
This lesson will cover the following learning objectives:
What is a flap? A flap is the area of soft tissue that is cut by a surgical incision in order to provide access to underlying tissues.

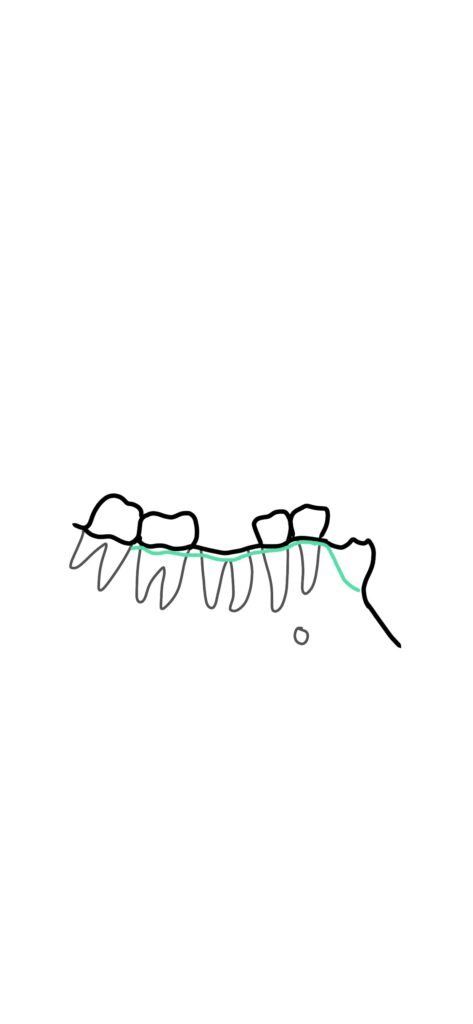

The envelope flap is a one-sided, sulcular flap which is used in cases which require minimal bone removal. It can also be used for superficial retained roots and to access bony prominences.
Almost all maxillary flaps are envelope flaps as the concave surface is easily displaced for adequate access.
In dentate patients the surgical incision is along the gingival crevice both anterior and posterior to the site of surgical extraction.
In edentulous patients, the incision is made along the crest of the ridge. it is important to consider the position of the mental foramen as bone resorption over time can alter the position of the mental foramen to one that is more superficial.
The two-sided flap is a '3 cornered flap' that is essentially an envelope flap with a relieving incision either anterior or posterior.
It is used in cases of surgical extraction that require reflection of the flap to enhance access to the surgical site in an apical direction.
Variations of this flap are often used in surgical extraction of lower third molars and can often be referred to as a triangular flap.
It is more appropriate to place a relieving incision anteriorly – to increase vision and access, as well as making it easier to suture at the end of the procedure. Exceptions to this rule can be made in the aesthetic zone, whereby it would be sensible to place a relieving incision posteriorly prevent any possible scarring from being visible.
The three-sided flap is a 'four cornered flap', that is essentially an envelope flap with relieving incisions both anterior and posteriorly.
It is also known as an apically repositioned flap.
Advantages of this flap design is best access and reflection, indicated in cases of surgical endodontics.
During mandibular surgical extractions, it is important to be aware of;
(these may be explored in further detail in the Clinical Anatomy section of the website)
The mental nerve emerges from the mental foramen in a variable region near the apices of the lower premolars. The exact location can differentiate between patients, also varying between race and age.
It is essential to have a pre-operative radiograph that confirms its location prior to incision.
The mental nerve lies within the buccal soft tissues and will be retracted with the flap, therefore it is important to consider the amount of pressure applied to the retractor to prevent a crushing injury to the nerve.
No relieving incision should be extending down to the area between first and second premolars. The flap should be extended to avoid this area.

The lingual nerve lies with the chorda tympani adjacent with the medial surface of the body of the mandible, therefore all incisions to allow access to the posterior mandible must be made buccally.

When considering only soft tissue management of the surgical extraction of posterior mandibular teeth, the IAN is not considered to be at risk due to it being encased in the mandibular canal within the body of the mandible.
However, during extraction it can be compromised depending on location and technique, therefore careful consideration needs to be undertaken during planning of the extraction.
This is why risk of temporary/permanent nerve damage needs to be explained to the patient during extraction of lower wisdom teeth.
During maxillary surgical extractions, it is important to be aware of:
The hard palate is innervated and oxygenated by the greater palatine structures, therefore an envelope flap is usually recommended
If a vertical relieving incision is required for access, then do so at the anterior end rather than posteriorly as a precaution to prevent injury to the greater palatine artery which may result in active bleeding.
If an anterior flap is to be reflected, the greater palatine nerve can be safely cut at the level of the foramen and application of pressure can control bleeding. The nerve may regenerate however the mucosa innervated by the nasopalatine nerve is over a small area so the patient may not largely notice a difference in sensation, however it would be appropriate to advise them of all possible consequences.
Principles to adhere to when designing a flap are important to consider, preventing post-operative complications and ensuring rapid and efficient healing.

You should now be able to understand and apply the principles of flap design on your clinics!

